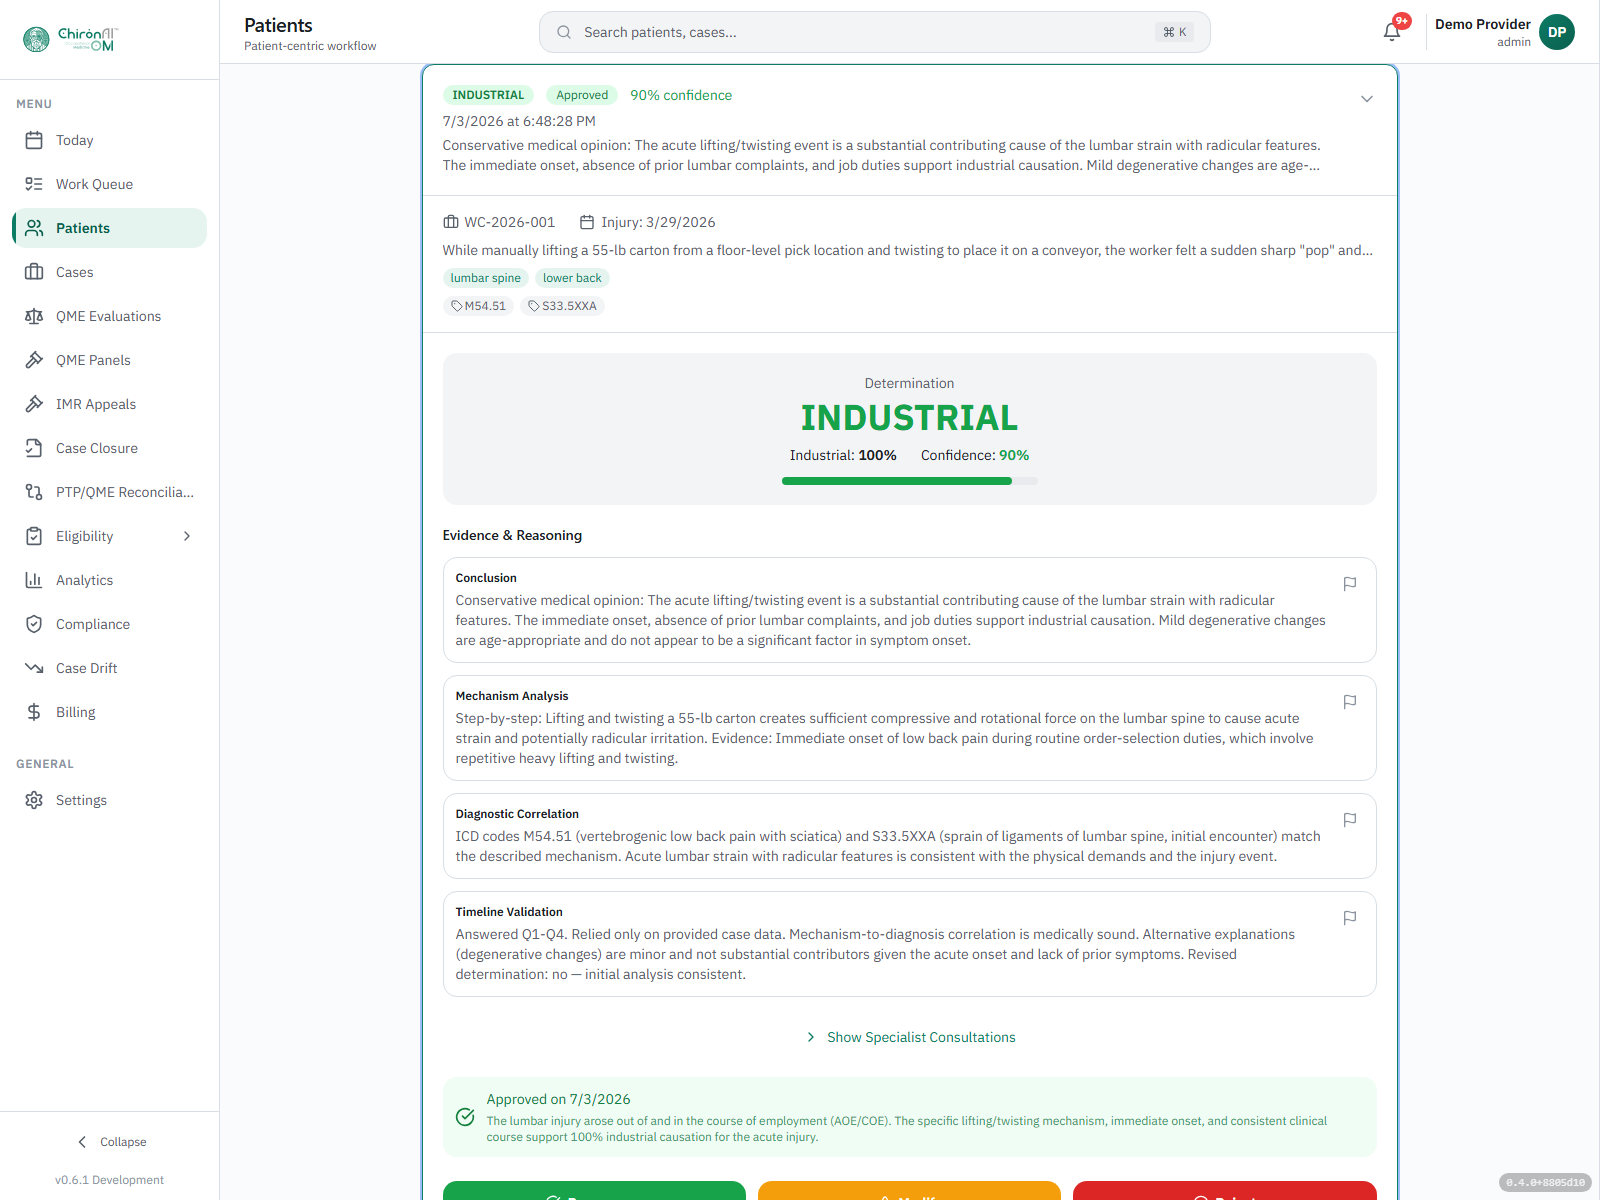
Decision support. ChironAI drafts the AOE/COE causation and apportionment analysis for the treating physician. The physician evaluates the reasoning, edits, and signs the determination. ChironAI does not make a regulatory clearance claim; see Disclosures.
An opinion that does not survive review was free work.
Causation and apportionment is where a California workers’-compensation report gets thrown out. Labor Code §3600 asks whether the injury arose out of and in the course of employment; §§4663–4664 ask how much of the disability is industrial. §4663(c) requires the physician to explain how and why, and under Escobedo an opinion that does not is not substantial evidence — which means it is not evidence. The case then turns on the report written by whoever did explain.
The failure is almost never medical judgement. It is a percentage that was never tied to a finding, an offset asserted rather than proved, a citation nobody checked. ChironAI™ OM names each of those before the report is signed, and refuses to put a citation in front of a physician that it cannot trace to something it was actually given.
Apportionment computed the way a workers’ compensation judge actually checks it — three prongs, audited, not asserted.
Seven named ways an apportionment opinion fails.
Before the draft reaches the treating physician, it is reviewed against §§4663–4664 and the controlling case law for legal sufficiency, factor by factor. These seven are not headings we wrote for this page — they are the flag names in the product’s own output contract, and each one points at a specific factor rather than at the report in general.
missing_reasoning
A percentage with no “how and why”
§4663(c) requires each attribution to be explained with specific medical reasoning that ties the cause to the level of disability. A bare number is non-compliant on its face, and it is the single most common reason an apportionment opinion is set aside.
not_substantial
A factor that is merely present
Apportionment runs to substantial causes of permanent disability. A finding that is coincidental, incidental or simply visible on a film is not a substantial factor, and apportioning to it invites the whole analysis to be re-opened.
weak_evidence
Evidence that will not carry the number
Imaging, exam findings and records have to be sufficient to support each percentage. An unsupported percentage is indefensible whether or not anyone notices at the time it is written.
percentage_indefensible
A number that cross-examination would expose as arbitrary
The test applied is whether a QME challenge or a cross-examination at the Appeals Board would show the figure to be arbitrary. That question is asked of the draft while it can still be changed.
escobedo_insufficient
A conclusion dressed as an analysis
Escobedo v. Marshalls requires the “how and why” to be stated in reasonable medical probability on a reasoned, non-speculative basis. Conclusory labels and ipse dixit percentages fail the substantial-evidence standard, and a report that fails it is not evidence at all.
strait_brodie_prong_missing
An offset claimed without all three prongs
A §4664 prior-award offset needs a prior adjudicated award, overlapping disability, and a permanent-disability-to-permanent-disability comparison. Each prong is checked independently; the offset is not legally supportable until every one of them is established.
hikida_misapportionment
Treatment-caused disability written off as non-industrial
Disability flowing from treatment of the industrial injury — a surgical complication, an adverse outcome of care — is compensable as a consequence of that injury. The flag fires when a factor apportions it away without distinguishing disability from the original injury from disability from its treatment.
The review returns a sufficiency score from 0 to 100 alongside the flags. Eighty and above is the product’s own threshold for “ready for physician review” — not for filing, and not for signature. Below it, the flags say which of the seven the draft tripped and on which factor. The reasoning is advisory and is not legal advice; the physician decides what the report says.
A named factor, or nothing.
§4663 apportionment is to causes, and a cause has to be identified before it can carry a percentage. The analysis works from a fixed vocabulary of seven factor types, requires at least one current-industrial factor on every case, and requires the percentages to sum to 100. There is no residual bucket to hide an unexplained share in.
Current industrial
current_industrialThe work injury or exposure at issue. Always present — the analysis cannot return without it.
Prior industrial
prior_industrialAn earlier compensable work injury to the same body part. The one that opens the §4664 question.
Degenerative
degenerativeAge-related change: disc disease, osteoarthritis. Present on the film is not the same as substantial.
Constitutional
constitutionalGenetic or anatomical predisposition, where the record actually establishes one.
Non-work trauma
non_work_traumaAn injury or accident away from work, dated and sourced or not asserted at all.
Lifestyle
lifestyleObesity, smoking, sedentary habits, where they contribute to the condition rather than merely accompany it.
Other
otherAny further identifiable contributing factor, named rather than folded into a residual.
Must review before final
Decision-support output. Clinician review and attestation required before this content is signed into the chart.
15% apportioned to pre-existing degenerative disc disease documented on prior imaging; 85% to the industrial lifting injury, per the treating-physician analysis.
Labor Code §4663 (causation-based apportionment); Escobedo substantial-evidence standard.
Where the record will not support a confident split, the analysis still returns one — at lower confidence, with the missing evidence listed as gaps. A physician can act on a stated gap. A silently confident number is the thing that gets discovered in deposition.
Three prongs. Audited. Not asserted.
A prior permanent-disability award is the fact most often used to argue a smaller number, and it is also the fact most often used badly. Under Brodie and Strait the offset needs three things established independently, and under Kopping the existence of a prior award proves only that the prior disability existed — the burden of proving that it overlaps the current one sits with the party claiming the offset. The engine checks the prongs in order and writes its derivation to the case record.
Must review before final
Decision-support output. Clinician review and attestation required before this content is signed into the chart.
- Prong 1 — Prior adjudicated awardEstablished
Is there a prior permanent-disability award of record — not merely prior findings, prior symptoms or prior treatment?
Prior award CT-2022-04410 issued 2023-08-02. No petition for reconsideration on file; the appeal window closed with no action taken.
- Prong 2 — Overlapping disabilityEstablished
Does the prior disability overlap the current one in body part or region and in impairment scope?
Prior award rated the right shoulder (rotator-cuff pathology). Current claim: a right shoulder labral tear from a fall. Overlap established on the record rather than inferred from the body-part code.
- Prong 3 — PD-to-PD offsetEstablished
Is the offset taken from current permanent disability to prior permanent disability — not to prior conditions or pathology?
Current PD rating 22% − prior award 12% = 10% apportioned PD. Percentage against percentage, per Brodie — never a dollar figure.
Apportioned permanent disability
10%
Computed, not generated. The same inputs reproduce the same output on replay, and the derivation — which prong, on what finding, at what time — is written to the case record with the actor and a signature chained to the entry before it.
A prong that cannot be established does not quietly become a zero. It is returned as an unmet prong with the reason, and the offset is reported as not legally supportable until it is met — which is the finding you want on the record before the other side makes it for you. Synthetic case; no screen on this site shows a real patient or a real practice.
The case gets argued against before you sign it, not after.
The determinations on a case — causation, apportionment, impairment — can be war-gamed on demand. The reasoning runs in two passes. In the first it takes the other side: a defence QME, an applicant attorney, a utilization-review reviewer, a judge at the Appeals Board, hunting for the strongest concrete attacks on what you are about to put your name to. In the second it answers each one from the record, citing the specific evidence that answers it.
It is instructed not to invent evidence, exam findings, imaging, dates or legal authorities to close a gap. Where the record has no answer, the honest outcome is the one it is told to return.
status: answered
Fully answered
The record holds a specific, evidence-backed rebuttal, and the evidence that answers the challenge is cited by name.
status: manage
To manage
Defensible, but on weaker footing than you would want it to be if this is the point the other side chooses to press.
isExposure: true
Unanswered
The record does not answer the challenge. The gap is stated plainly rather than papered over, with a concrete next step a physician could take to close it.
An open exposure blocks the packet.
Each exposure can be held as provisional on the record. While one is held, the system refuses to submit the defence packet and says why: close or release the exposure first. The counts that drive that refusal — answered, to manage, unanswered — are recomputed on the server from the surviving challenges, so the summary at the top can never disagree with the list underneath it.
The result bundles into a defence packet: every challenge, every rebuttal, every cited source, on the audit-linked record. It is an advisory draft. A physician reviews each challenge and rebuttal before any reliance on it, and the packet is not a legal filing and not legal advice.
It cannot cite a case that does not exist.
The worst failure mode in a medical-legal document is not a weak argument. It is a confident citation to an authority that was never decided — which is career damage, not a revision. So the case law available to a causation or apportionment analysis is not open text. It is a registry of ten authorities, each with its rule, its reporter citation and the statutes it governs. When the reasoning names an authority, the name is checked against the registry and anything outside it is discarded before the output is assembled. There is no path by which an invented case reaches the draft, because there is no field an invented case can survive in.
A registry also keeps the law current in a way a prompt does not. Vigil v. County of Kern displaced Kite as the governing standard for adding impairments; the registry carries both, with Kite marked historical, so a report cannot lean on a superseded standard without the superseding one sitting next to it.
Escobedo v. Marshalls
An apportionment opinion must constitute substantial evidence: the physician explains, in reasonable medical terms, how and why the percentages were reached. Bare conclusions fail.
Brodie v. WCAB (2007) · Strait v. WCAB (2012)
The §4664 prior-award offset requires all three prongs: a prior adjudicated award, overlapping disability, and a PD-to-PD comparison.
Kopping v. WCAB (2006)
A prior award conclusively establishes that the prior permanent disability existed — but the defendant still bears the burden of proving overlap. Absent proven overlap, no offset applies.
Hikida v. WCAB (2017)
Disability caused by treatment of the industrial injury is compensable as a consequence of it; the report must distinguish disability from the injury from disability from its treatment.
Benson v. WCAB (2009)
Each distinct industrial injury gets its own causal share and its own separate rating and award — unless the physician expressly says the injuries cannot be parcelled out, and explains why.
Almaraz / Guzman (2009)
A physician may depart from the strict AMA Guides rating where it does not reflect the impairment, supported by objective findings and still working within the Guides framework.
Vigil v. County of Kern (2024) (en banc)
The binding standard for adding impairments instead of combining them: an ADL-by-ADL showing, both results presented, and the bare word “synergy” is insufficient.
Athens Administrators v. WCAB (Kite) (2013) — historical
The historical origin of add-versus-combine, held in the registry as superseded so that a report cannot quietly rely on it as the governing standard.
Wilson v. State of California CAL FIRE (2019) (en banc)
The five-factor test for whether a physical injury is “catastrophic” under §4660.1(c)(2)(B), which reopens psychiatric add-ons for dates of injury from 2013.
Baker v. WCAB (2011)
The §4659(c) cost-of-living increases commence on the January 1 after the payments commence — not the January 1 after the date of injury.
The same discipline applies to the record, not only to the case law
Every document citation on an apportionment factor is checked against the set of extractions the reasoning was actually given. A citation to a source that was not in that set is removed — not flagged, not footnoted, not left for a reviewer to catch on a Friday afternoon. The reasoning runs on Eve-Healthcare™ F5/reasoner, and this is the guardrail that stands between a reasoning engine and a filed document. How we prevent fabrication.
“Presumption, therefore no apportionment” is false.
Where the worker is a firefighter, a peace officer or another safety member, a §3212 presumption may apply. The apportionment screen raises the question rather than answering it — member class, qualifying service and the injury date decide it, and none of those is a job title.
Two lists, not one
§5402(b)(2) shortens the compensability presumption to 75 days across two ranges of the §3212 family. §4663(e) disapplies the apportionment determination for an explicit enumeration of sixteen sections. They are not the same set, and the product stores them as two lists because they are two lists.
§3212.15 is the one that catches people
The PTSD presumption was added in 2019; §4663(e) was last amended in 2016. A §3212.15 case therefore carries the 75-day clock and still owes a full §4663(a)–(c) apportionment determination. Treating the presumption as removing the question leaves a required element out of the report.
The ranges are not arithmetic
Reading "§3212.9 to §3213.2, inclusive" as a numeric comparison silently drops §3212.10, §3212.11 and §3212.12, all of which sort below §3212.9 as decimals. The statute runs over the code’s printed order, so both lists are stored as resolved enumerations and nothing does arithmetic on a section number.
Two years later, it still reconstructs.
A causation or apportionment analysis is deposed long after it is written, and the question is always the same one: on what, exactly, did you base that. Every analysis is versioned; an amendment is a new version and the original stays verifiable. Each step — the verification pass, the specialist consultation, the §4664 computation — is stamped with the actor, the time and a signature chained to the step before it.
Nothing is treated as authoritative until the treating physician signs it, and that is enforced at the data layer rather than by a button that can be skipped. The signature is verifiable against a public endpoint, so anyone holding the document can establish that it has not been altered since attestation.
Causation is rarely only a medical question, and the specialist consultation that sits behind these determinations is its own subject. How the Digital Employees consult on a case →
Bring the report you are least comfortable with.
We will run the legal-sufficiency review and the pre-mortem against a case of your own and show you what comes back — which factor has a percentage with no reasoning behind it, which prong of an offset is not actually established, and what the other side would open with. That is a more useful forty minutes than any slide we could show you.
Bring one month of EORs — you keep the findings either way.
See the full capabilities inventory